The headache
AI in medicine
But doctors who understand AI
will replace those who don’t.
This isn’t a talk about replacing medicine with AI.
It’s about learning where AI helps—and where it can hurt.
Your guide



Join at
slido.com
#3474 854
Active poll
The good
AI + Pharmacology
Clinical reality
Relative visual emphasis only · not a statistical ranking
What are doctors asking AI?
“Summarize this paper.”
“Explain this mechanism.”
“What are the differential diagnoses?”
“Check these drug interactions.”
“Explain this lab result.”
“Draft patient instructions.”
“What dose should I prescribe?”
Audience pulse check
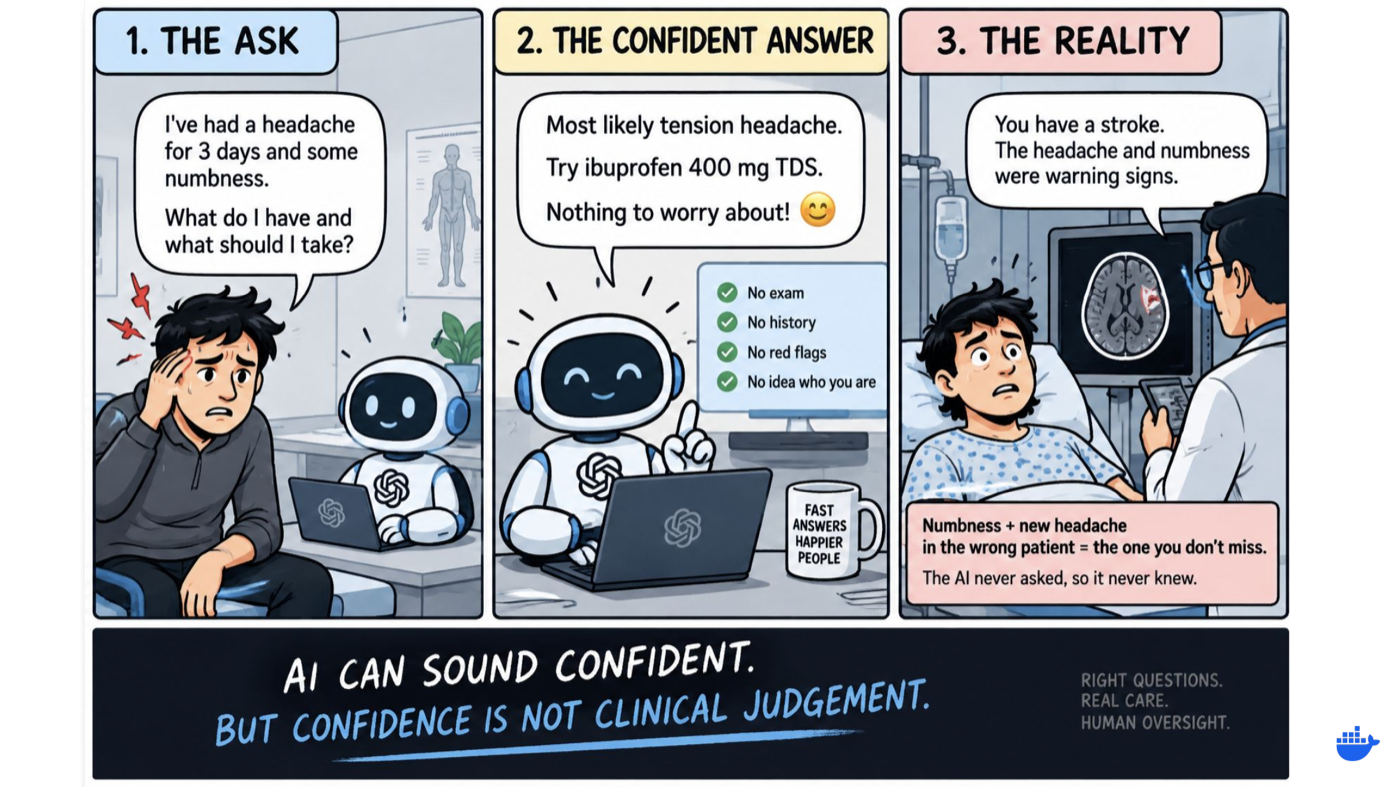
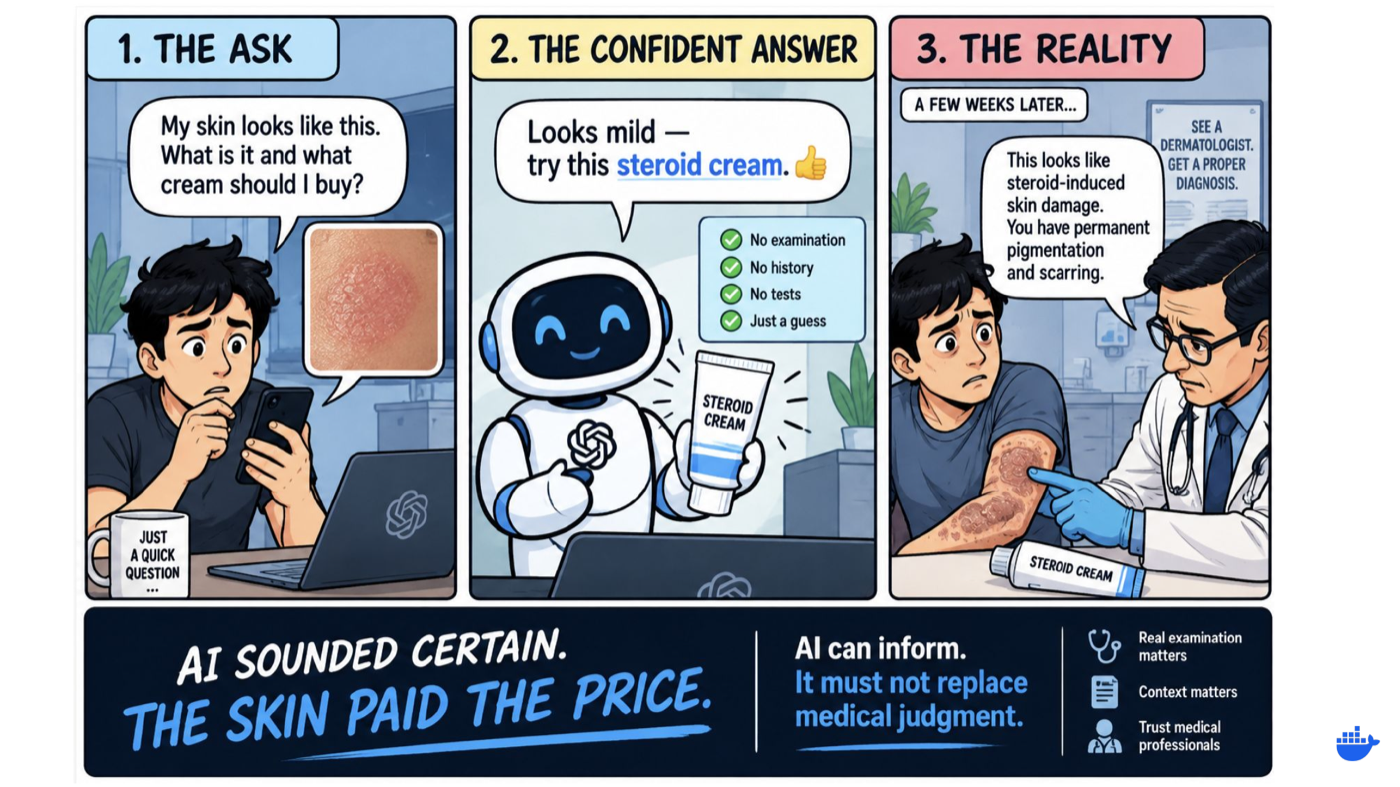
The bad · the confidently wrong
When a plausible answer becomes a clinical risk.
Under the hood
Designing safer behavior
Major reveal
What if the medical AI ran locally instead of sending everything to a public chatbot?
Local execution improves control. Security still depends on the surrounding system.
Model ecosystem
A large ecosystem includes models targeting medical Q&A, radiology, pathology, dermatology, biomedical language, imaging, clinical text, drug discovery, protein science, and embeddings.
Results reflect this curated teaching demo—not a live ecosystem count.
Featured family
A family of open models designed for medical text and medical image comprehension.
A healthcare-focused model still needs validation for its intended use.
Hands-on concept
$ docker model run hf.co/google/medgemma-4b-ptDownloading model layers…Starting local inference…✓ Interactive session ready
Hardware needs vary. Larger models require substantially more RAM or VRAM. Quantized variants can reduce requirements when available and appropriate.
Real-world proof
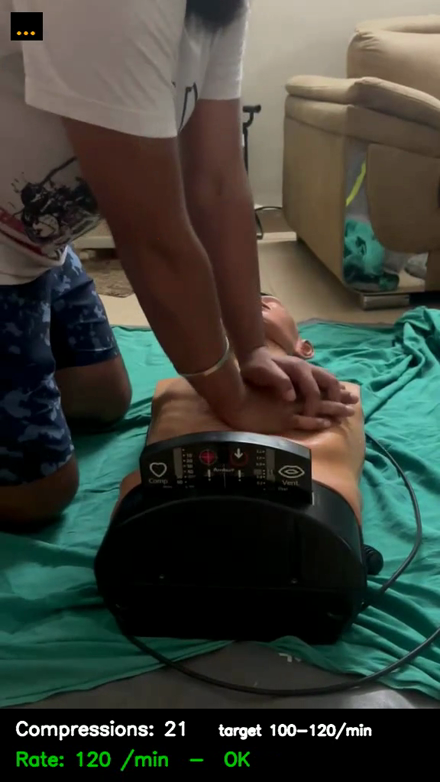
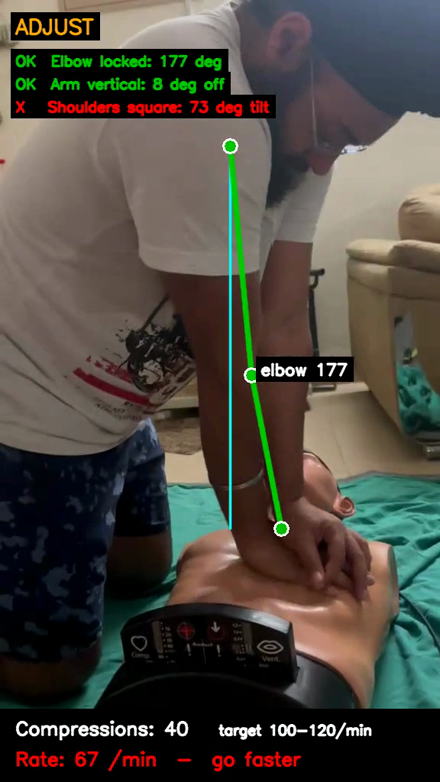
A real project: an AI coding agent built a live CPR coaching tool—pose detection, compression rate, and arm-angle feedback—end to end.
An AI coding agent built this real-time CPR coaching tool—pose tracking, compression-rate feedback, and arm-angle correction—end to end, in about ten minutes.
Interactive centerpiece
Questioning improves context. It does not turn a language model into a clinician.
Dedicated teaching mode
Mechanism
A receptor-level explanation. Select a lens to inspect the same concept.
Patient-specific dose questions require indication, age, route, formulation, organ function, medicines, and other clinical context.
Architecture choices
Provider-dependent
Higher control; system-dependent
Provider catalog
Chosen by your team
Usually limited
Potentially extensive
Often opaque or mixed
Can be curated
Variable
Can be designed in
Usually no
Possible
Network-dependent
Hardware-dependent
Subscription / usage
Hardware + maintenance
Shared with provider
Your organization owns it
Shared
Primarily yours
The right equation
Fast, but can miss context.
Clinical judgment, but limited time and information bandwidth.
Human judgment + computational assistance.
Keep these
Never confuse confidence with correctness.
Ask for context before answering.
Verify clinical claims and citations.
Protect patient information.
Know which model you are using.
Understand the model’s limitations.
Keep a qualified human responsible for clinical decisions.
The final prescription